The therapeutic alliance according to the evidence: how much it really weighs
There is a question that goes through decades of research into psychotherapy: what really makes a treatment work? Technique, theoretical orientation, diagnosis, relationship. Above all, there is debate. But on one factor there is a remarkably solid empirical consensus: the therapeutic alliance.
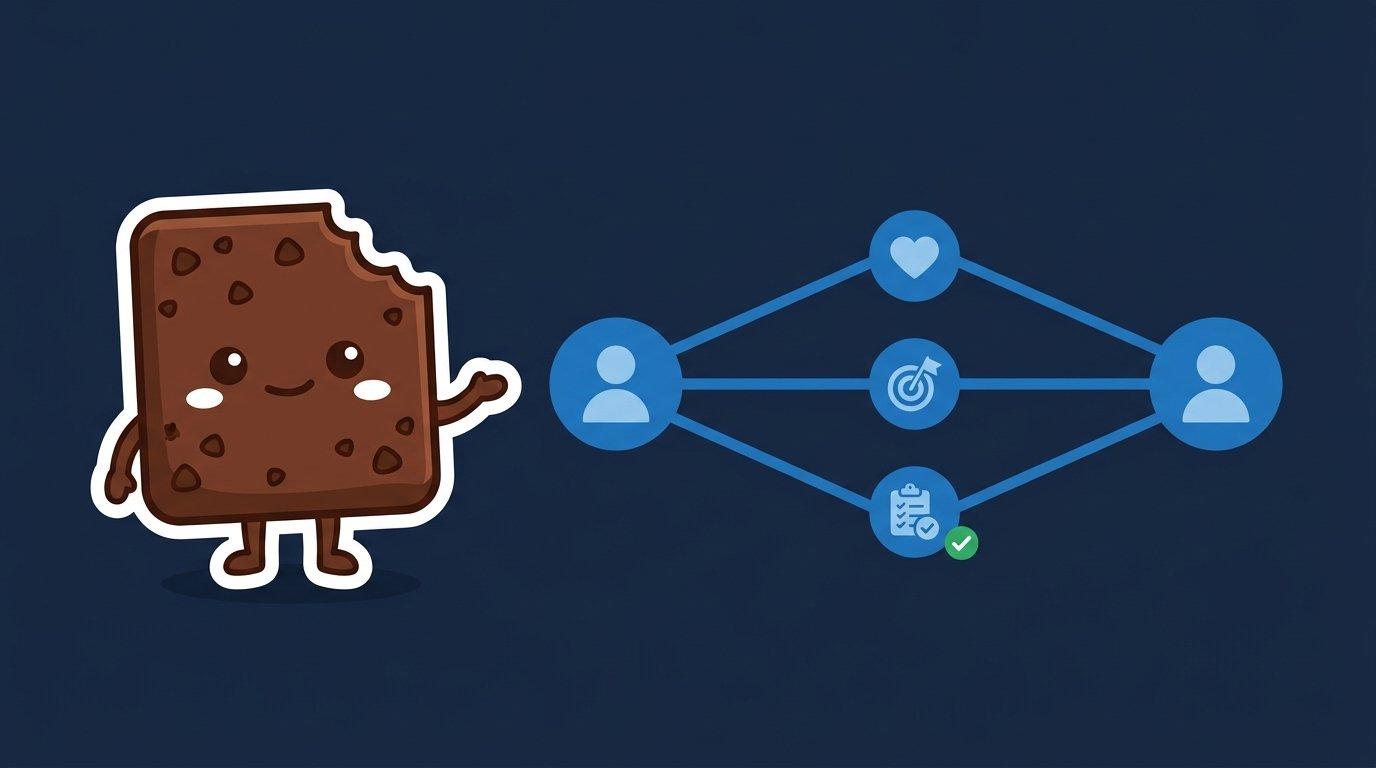
The alliance (or therapeutic bond, or working relationship) is not "feeling good." In Edward Bordin's classic definition it has three components: the emotional bond between patient and therapist, the agreement on the objectives of treatment, and the agreement on tasks to achieve them. It is a collaboration with leadership, not just a good chemistry.
The interesting question is not whether the alliance matters, that hardly anyone disputes it, but how much it matters and what the quantitative evidence says about it.
TL;DR
- The therapeutic alliance is one of the most consisting predictors of the outcome in psychotherapy.
- The largest meta-analysis to date (295 studies, more than 30.000 patients) found an association of r ≈ 0.28 between alliance and outcome.
- The effect is robust: sustained through different orientations, measurement types, disorders and countries.
- It's an association, not a pure causality test, but it's one of the most replicated findings in the whole field.
What the evidence says
The reference study is the meta-analysis of Flückiger, Del Re, Wampold and Horvath (2018), published in Psychotherapy. It is the most ambitious synthesis carried out on the subject: it gathered 295 independent studies and more than 30.000 patients, covering face-to-face and online psychotherapy, from 1978 to 2017.
The central result: the aggregate correlation between alliance quality and treatment outcome was r ≈ 0.28.
This number deserves context. In psychotherapy research, where the results depend on dozens of intertwined factors, a correlation of this magnitude, replicated in hundreds of studies, is one of the most stable findings that exist. The alliance explains a modest but very consistent portion of why some patients are doing better than others.
Note
An R of 0,28 does not mean that the alliance "makes" the 28% of work. It is a measure of association between the force of the labor bond and the outcome. The remarkable thing is not the magnitude but the consistency: hundreds of studies, with different methods, pointing in the same direction.
And perhaps the most important thing for practice: the effect remained table through moderators. It did not depend substantially on the therapist's theoretical orientation, the type of instrument used to measure the alliance, the treated disorder or the country. Whatever your framework, the quality of the working relationship is associated with how treatment ends.
What the evidence DOES NOT say
Here it is necessary to be precise, because the alliance is sometimes cited as settling all the debates:
- No experimental causality test. No patients can be randomly assigned to a "strong" or "weak" alliance, so the evidence is correlated and longitudinal, not experimental. That said, the meta-analysis itself tested whether the association was just a reflection of early improvement (adjusted by initial severity and previous changes) and found that it held almost the same (r went from 0,25 to 0,22), which supports that the alliance functions as a facilitating factor and not as a mere byproduct of progress.
- It does not say that the technique does not matter. That the alliance is robust does not make specific interventions irrelevant. Much of a strong alliance is precisely the agreement on tasks that make sense to the patient.
- It is not a permission to neglect the method. "Total, what heals is the bond" is a lazy reading. The evidence says that the bond weighs, not that it is the only thing that weighs.
What does it mean in your clinical practice
The good news is that the alliance is not a fixed trait of the therapist: it is something that is built, monitored and, when damaged, repaired.
- Work the agreement, not just the weather. The emotional bond is a three-legged one. Check explicitly that patient and therapist share where they are going (objectives) and how they are going to get (tasks) is central to building alliance, not an initial process.
- Pay attention to ruptures. Moments of tension, disagreement or distance in the relationship are frequent and are not a failure: they are opportunities. The literature on repair of ruptures shows that addressing them openly can strengthen the bond more than if they had never appeared.
- Ask for the relationship directly. Many patients will not spontaneously say that something about the bond does not work. Open the door ("How do you come feeling these sessions?, is there anything you would like us to work differently?") makes visible what otherwise goes silent, many times in the form of abandonment.
- Consider measuring the alliance. As with the monitoring of results, a short scale of alliance applied from time to time can detect a deterioration of the bond before it is translated into an empty chair.
Council
A rupture of alliance is rarely announced. It is noticed in subtle signs: the patient who participates less, who arrives late, who "is all right" when clearly not. Name what you see, without accusing, usually reopens the conversation: "I noticed you a little quieter today, do we talk about it?"
Killings and limitations
- Association is average. That the alliance despite population level does not mean that it is the decisive factor in each individual case. In some treatments other elements will weigh more.
- Measuring the alliance has its own biases. Most measurements are based on the patient's report, which may be influenced by his or her state of mind of the day or the desire to please the therapist.
- Correlation is not a recipe. Knowing that the alliance matters doesn't automatically tell you how to build a better one in a specific case. That's where your training, your supervision and your clinical experience keep coming in.
In summary
Of all the factors studied in psychotherapy, the therapeutic alliance is one of those that best resists the passage of the years and the accumulation of studies. Not because it is magical, but because a patient who trusts, who understands where he is going and who agrees with how to get there, is a patient who sustains the treatment and works in it.
None of this is done by a machine. The link is, by definition, human. That is why the role of a tool like Brauni is exactly the reverse to which is sometimes feared: when dealing with the record and documentation, it releases your attention for the only thing that cannot be delegated, which is to be present with the patient. AI prepares the draft of the note; the link is built by you.
References
- Flückiger, C., Del Re, A. C., Wampold, B. E., & Horvath, A. O. (2018). The alliance in adult psychotherapy: A meta-analytic synthesis. Psychotherapy, 55(4), 316-340. doi.org/10.1037/pst0000172
- Bordin, E. S. (1979). The generalizability of the psychoanalytic concept of the working alliance. Psychotherapy: Theory, Research & Practice, 16(3), 252-260. doi.org/10.1037/h0085885
Free Brauni test for 30 days, no card
Automatic session notes, digital medical records and more.
Start for freeRelated articles

Based on Evidence
Does online therapy work just like face-to-face therapy? What does the evidence say
Meta-analysis with thousands of patients compare video and face-to-face psychotherapy: equivalent results and therapeutic alliance without differences. What does it imply for your clinical practice.

Based on Evidence
How many sessions do you need? Evidence of dose and frequency in therapy
Dose-response research shows improvement curves, optimal session ranges, and an uncomfortable finding of weekly frequency. What does it mean when planning treatments.

Based on Evidence
Treatment of Trauma: What the Evidence Says About EMDR and Trauma-Focused TCC
A network of 90 trials and 6.560 patients compared 22 treatments for post-traumatic stress. What EMDR and trauma-centered CCT show, and what it means when choosing approach.